หน้าแรก
» เทคโนโลยี
»
The Ethical Dilemmas of AI in Healthcare: A Beginner’s Guide to Responsible Use
The Ethical Dilemmas of AI in Healthcare: A Beginner’s Guide to Responsible Use
Artificial intelligence is already part of healthcare in ways that range from image analysis and risk prediction to documentation support and patient-facing chat systems. The ethical question is not simply whether AI is “good” or “bad.” It is whether a particular system improves care without creating unacceptable risks for patients, clinicians, or communities.
For a newcomer, the most useful approach is to follow the decision path in order: understand what the system actually does, identify who can be affected, check the evidence and data behind it, define the human role, and decide how problems will be detected and corrected. This article explains that path without assuming a technical background.
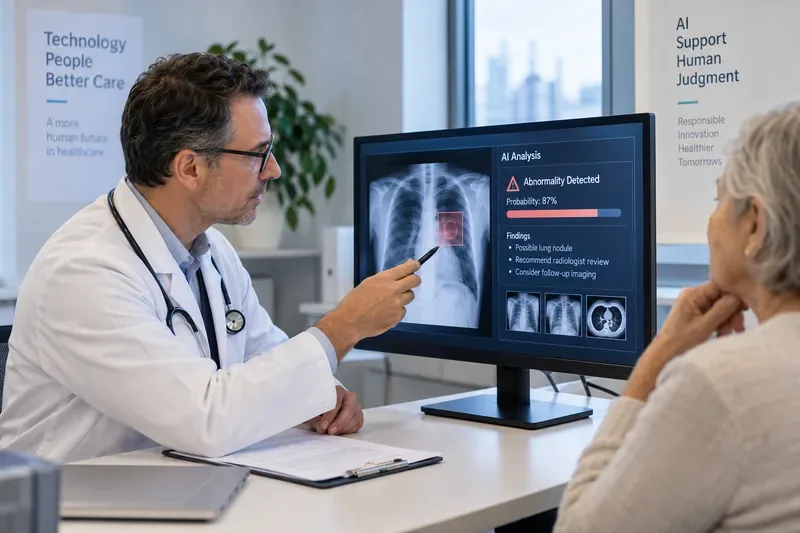
A clinician reviews an AI-assisted medical image with a patient, illustrating why explanation, human judgment, and patient involvement remain central when algorithms influence care.
First, know what “AI in healthcare” actually means
Artificial intelligence (AI) is a broad term for computer systems that perform tasks associated with human reasoning, pattern recognition, prediction, or content generation. Machine learning is a subset of AI in which a model learns patterns from data rather than following only hand-written rules. Generative AI produces new content such as text, images, or summaries. In medicine, a generative system might draft a clinical note, answer a patient question, or summarize a chart.
These categories matter because the ethical risk depends on the task. A system that formats appointment notes does not pose the same danger as a model that influences cancer screening, triage, drug dosing, or access to care. Likewise, the word “AI” does not mean a system is autonomous. Many tools are designed to support a clinician rather than replace one.
What to prepare before evaluating or using a healthcare AI system
Before asking whether an AI tool is ethical, write down its intended use in one sentence. For example: “This system ranks chest X-rays for radiologist review” is much more useful than “This is an AI radiology platform.” The intended use tells you what kind of error matters, who is affected, and how much human oversight is needed.
Question to answer
Why it matters
What a stronger answer looks like
What decision does the system influence?
Risk grows when output affects diagnosis, treatment, triage, or access.
A narrow, documented use case with clear limits.
Who was represented in development and testing data?
Performance may change across age, sex, race, geography, disease severity, devices, or care settings.
Evidence includes clinically relevant subgroups and external validation.
What happens when the AI is wrong?
A small error rate can still matter when consequences are severe.
Defined human review, escalation, and fallback procedures.
What data enters or leaves the system?
Health data can reveal highly sensitive information.
Data minimization, access controls, retention rules, and clear vendor responsibilities.
Can performance change after deployment?
Models, workflows, patient populations, and clinical practice can drift over time.
Version control, monitoring, revalidation, and change management.
The core ethical dilemmas
1. Accuracy versus harm
A model can be statistically impressive and still be unsafe in a particular workflow. A false negative may delay treatment; a false positive may trigger anxiety, invasive testing, or unnecessary cost. The right metric therefore depends on the clinical purpose. “Accuracy” alone can hide important tradeoffs between sensitivity, specificity, calibration, and subgroup performance.
A useful beginner rule is to ask what the worst plausible error is and how it would be caught. If the answer is “the clinician will notice,” the next question is whether the workflow actually gives the clinician enough information and time to notice.
2. Bias and unequal outcomes
Algorithmic bias is a systematic pattern that produces unfair or clinically inappropriate differences between groups. Bias can enter through unrepresentative training data, historical inequities, measurement differences, or the choice of a target variable.
A well-known example comes from a 2019 Science study of a widely used population-health algorithm. The researchers found racial bias because the system used healthcare spending as a proxy for health need. Since unequal access can lead to lower spending even when illness is substantial, the proxy distorted who was identified for additional care. The lesson is broader than that one algorithm: a convenient target can encode existing inequity even when race is not explicitly included as an input.
Before deployment, ask whether the tool has been evaluated on the population and setting where it will be used. After deployment, compare outcomes across clinically relevant groups rather than assuming that one overall performance number is enough.
3. Privacy versus data hunger
AI systems often improve when they receive more data, but healthcare ethics does not treat maximum data collection as an automatic good. Privacy is connected to dignity, autonomy, trust, and the possibility of harm from unauthorized access or secondary use.
ในสหรัฐอเมริกากฎ HIPAA Security Ruleใช้บังคับกับข้อมูลสุขภาพที่ได้รับการคุ้มครองทางอิเล็กทรอนิกส์ซึ่งจัดเก็บโดยหน่วยงานที่อยู่ภายใต้ขอบเขตของ HIPAA และผู้ร่วมธุรกิจ แต่ไม่ใช่ทุกแอปพลิเคชันด้านสุขภาพหรือบริการ AI สำหรับผู้บริโภคจะอยู่ภายใต้ขอบเขตของ HIPAA กฎ FTC Health Breach Notification Ruleอาจใช้บังคับกับผู้ให้บริการบันทึกสุขภาพส่วนบุคคลและหน่วยงานที่เกี่ยวข้องบางแห่งที่อยู่นอกเหนือขอบเขตของ HIPAA ความแตกต่างนี้มีความสำคัญเมื่อตัดสินใจว่าข้อมูลผู้ป่วยที่ละเอียดอ่อนสามารถนำไปใส่ในเครื่องมือ AI ที่ผู้บริโภคใช้งานได้หรือไม่